

How to form sustainable prices during the transition of the Consumption Reforma Tributaria
Technical article • Updated on August 24, 2026
|
Central recommendation:
use costing by procedure and practical capacity, complement it with a contribution
margin, and simulate the IBS/CBS net of credits. A generic percentage
on revenue does not capture the economic reality of clinics,
offices, laboratories, and hospitals. |
Marli Voss Hartmann da Silva
Versátilis
Accounting Studies and Concepts
Executive summary
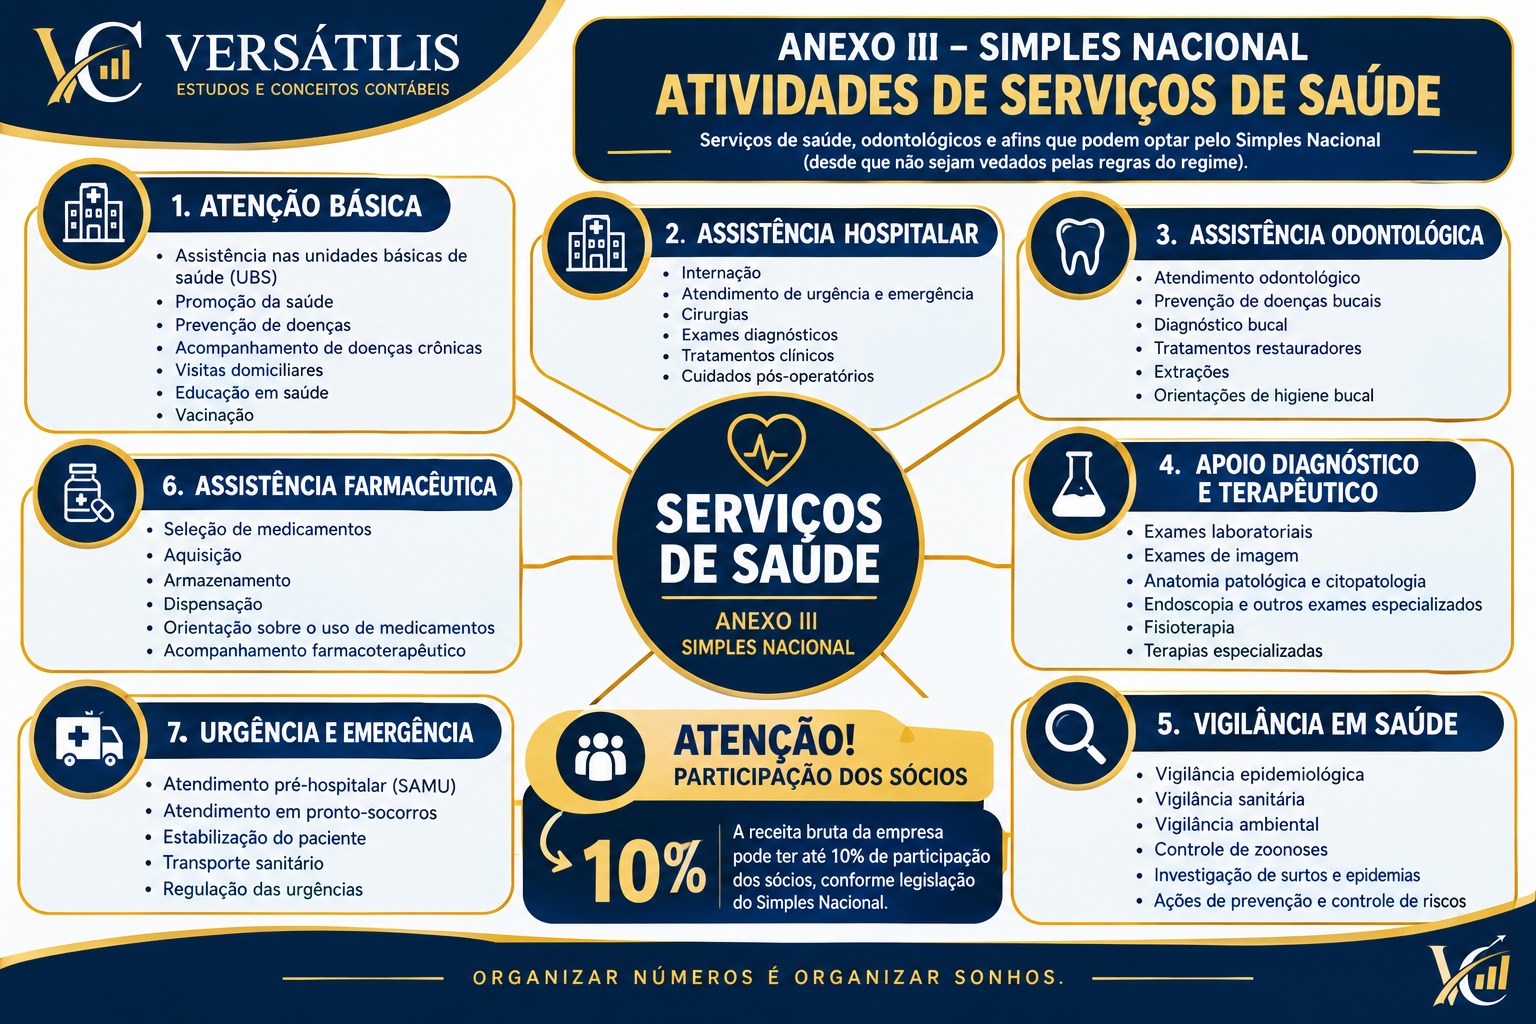
The tax reform changes the pricing logic in the health sector because IBS and CBS adopt a consumption taxation model with broader credits, exclusive incidence, and differentiated treatments. Complementary Law No. 214/2025 reduces IBS and CBS rates by 60% for health services expressly listed in its Annex III. This does not mean a final rate of 60%, but rather the application of 40% of the standard rate. Since the definitive standard rate depends on acts by the competent entities, the price should not be set based on a single estimate.
The best methodology is hybrid: (1) measure care costs per procedure; (2) allocate fixed costs based on practical capacity, rather than idealized occupancy; (3) add commercial expenses and desired margin; (4) estimate the IBS/CBS debit and the credits actually claimable; and (5) test scenarios by tax regime, client profile, and transition phase. The result is a technically defensible price, subject to review and aligned with the sustainability of care.
1. What really changes for healthcare
Constitutional Amendment No. 132/2023 created the constitutional basis for the new consumption taxation system. The main regulation came with Complementary Law No. 214/2025, subsequently adjusted by Complementary Law No. 227/2026. For health services listed in Annex III of LC No. 214/2025, art. 130 provides for a 60% reduction in IBS and CBS rates. Amounts disallowed by the medical audit of health insurance plans and not paid are not included in the tax base of these taxes.
The benefit must be confirmed by the classification of the service in the Brazilian Service Nomenclature (NBS) and by the operation actually provided. One should not assume that all revenue earned by a healthcare company receives the same treatment. Sale of products, leasing, administrative activities, ancillary services, medications, medical devices, and health care plans may follow different rules.
|
Important note |
Effect on pricing |
Recommended measure |
|
60% Reduction |
The service rate equals 40% of the applicable standard rate. |
Simulate more than one standard rate and document the premise. |
|
Non-cumulativity |
Eligible purchases can generate credits and reduce the net burden. |
Map suppliers, tax documents, and credit restrictions. |
|
Tax on Top |
IBS and CBS are not part of their own base and gain visibility in the fiscal document. |
Separate base price, highlighted tax, and total amount charged. |
|
Transition 2026–2033 |
Old and new systems coexist in stages, changing tax burden and obligations. |
Recalculate prices annually and avoid long contracts without a review clause. |
|
Heterogeneous revenue |
Not all revenue from a clinic or hospital is a health service under Annex III. |
Classify each revenue line, avoiding indiscriminate tax averaging. |
2. The safest methodology: price per procedure
The recommended method starts with the procedure, consultation, exam, session, or hospital daily rate. The goal is to find the unit economic cost before margin and taxes. To do so, the organization must maintain care and support cost centers, control room and team time, record material consumption, and use a realistic occupancy rate.
Define the pricing unit
Consultation, examination, session, procedure,
daily rate, therapeutic package, or monthly contract.
2. Gather direct costs
Proportional fees and assistance salaries, medications, materials, outsourced exams, charges, and disposables.
3. Allocate indirect costs
Reception, billing, cleaning, technology, maintenance, depreciation, rent, energy, and management.
4. Adjustment by practical capacity
Divide fixed costs by realistically available hours or appointments, deducting vacations, maintenance, absences, and normal idle time.
5. Include expenses and risks
Card fees, defaults, expected disallowances, commissions, contingencies, and administrative expenses.
6. Model net IBS/CBS
Calculate the debit on the transaction, subtract only credits supported by documents, and respect the taxpayer's regime.
7. Apply the margin and test the market.
Compare with perceived value, competition, agreement tables, elasticity, and payment capacity.
3. Managerial Formula for Pricing
For contracts in which the clinic needs to define a total price that absorbs proportional expenses, tax risk, and margin, the following management formula can be used:
|
Preço-base = Custo unitário / [1 − (despesas variáveis % + carga tributária líquida % + margem desejada %)] |
The “net tax burden” is a management premise: estimated IBS/CBS debit less eligible credits, expressed as a percentage of revenue. It does not replace fiscal tax assessment. When the fiscal document shows IBS/CBS as a separate item, the system must separate the transaction's base price, the tax amount shown, and the total charged, in accordance with current rules.
4. Practical example: multiprofessional clinic
Consider a consultation with the following hypothetical values. The clinic is under the regular IBS/CBS regime, the service was confirmed in Annex III, and management wants a 20% margin on revenue. The example is didactic and does not represent an official definitive rate.
|
Component |
Value/Rate |
Criterion |
|
Direct service costs |
R$ 90.00 |
Professional time and materials |
|
Allocated indirect costs |
R$ 45.00 |
Structure and support |
|
Fixed cost per practical capacity |
R$ 55.00 |
Realistic occupation |
|
Total unit cost |
R$ 190.00 |
Sum of costs |
|
Variable expenses |
8.0% |
Cards, Chargebacks and Billing |
|
Desired margin |
20.0% |
Margin on revenue |
|
Estimated IBS/CBS debit |
11.2% |
40% of the standard 28% scenario |
|
Estimated credits |
2.2% |
Appropriable credits/revenue |
|
Net tax burden |
9.0% |
11.2% minus 2.2% |
Calculation: R$ 190.00 ÷ [1 − (8% + 9% + 20%)]
= R$ 190.00 ÷ 0.63 = R$ 301.59. Thus, R$ 301.59 is the managerial price needed
to cover the adopted assumptions. If the estimated credits drop, the break-even
price rises; if the clinic increases occupancy or reduces denials, the unit cost
and the required price may fall.
5. Sensitivity analysis
Since the definitive standard rate should not be treated as a fixed number, management needs to work with scenarios. Keeping the other premises of the example unchanged, with credits equivalent to 2.2% of revenue:
|
Standard scenario |
Health rate (40%) |
Net burden after credits |
Managerial price |
|
26.5% |
10.6% |
8.4% |
R$ 298.74 |
|
28.0% |
11.2% |
9.0% |
R$ 301,59 |
|
30.0% |
12.0% |
9.8% |
R$ 305.47 |
Correct reading: The legal reduction improves health treatment, but the final effect depends on the level of the standard rate, credits, tax regime, cost structure, and the commercial possibility of passing costs on.
6. Simples Nacional, presumed profit and actual profit
The choice of regime remains decisive.
Companies under Simples Nacional remain subject to the specific rules of LC No. 123/2006 and to the options provided in the new system. It is not technically correct to automatically apply the estimated reduced rate of the regular regime to every service provider opting for Simples. Companies outside Simples, in turn, need to integrate IBS/CBS into the joint analysis of IRPJ, CSLL, payroll, withholdings, and sectoral obligations.
Simples Nacional: Compare the DAS burden, the potential for transferring credits to the client, the B2C/B2B mix, and any option provided for IBS/CBS. The decision should not consider only the nominal rate.
Lucro Presumido: Project
IRPJ and CSLL according to the applicable presumed bases, in addition to the transition from PIS/Cofins to CBS and from ISS to IBS. Monitor withholdings and contracts.
Actual Profit: Reconcile accounting and tax margins, take advantage of credits when legally permitted, and control documentation by cost center, establishment, and nature of the operation.
7. Sector particularities that must be included in the price
Disallowances and Default
Unpaid disallowances have a specific rule for exclusion from the base for the covered services, but they continue to affect cash flow, productivity, and contractual risk.
Labor-intensive
Payroll and pro-labore do not, as a rule, generate the same pattern of credits from taxed acquisitions. Labor-intensive service providers may have proportionally lower credits.
Assets and technology
Equipment, software, and maintenance require documentary and credit eligibility analysis, in addition to economic depreciation in the cost.
Agreements
Schedules, deadlines, disallowances, and packages can prevent immediate pass-through. The contract must provide for tax review and scope changes.
Private and B2B service
Individual patients do not take advantage of credits; acquiring companies may value the regularity of the credit.
Commercial strategy and pricing may differ.
Ancillary revenues
Parking, product sales, aesthetics services not otherwise classified, leasing, and other revenues must be classified separately.
8. 90-Day Implementation Plan
|
Deadline |
Action |
Delivery |
|
0–30 days |
Separate revenues by NBS/NCM, map cost centers, contracts, adjustments, suppliers, and fiscal documents. |
Tax and cost matrix |
|
31–60 days |
Calculate cost per procedure and practical capacity; estimate credits; create scenarios by tax regime and client. |
Price and Margin Simulator |
|
61–90 days |
Review contracts, discount policy, tax registration, NFS-e issuance, and indicators panel. |
New pricing and governance |
9. Indicators to review monthly
Pricing should be dynamic. It is recommended to track cost per procedure, contribution margin, occupancy rate, average service time, denial rate, average collection period, IBS/CBS debit, recognized credits, net tax burden, profitability per health plan, and variance between standard cost and actual cost.
Conclusion
The best way to price healthcare services under tax reform is not to add a generic percentage to the current price. It is to build a price per procedure based on reliable costs, practical capacity, commercial risk, margin, and taxation net of credits. The 60% reduction provided for healthcare services listed in Annex III is relevant, but it must be applied to the applicable standard rate and only after the correct classification of the transaction.
In 2026, a test year, the priority is to prepare registrations, tax documents, systems, contracts, and cost data. A clinic that knows its margin per service can adjust prices gradually, negotiate with health insurance providers on a technical basis, and prevent the tax transition from compromising financial sustainability or patient access.
|
Technical note: this article is for educational and managerial purposes. Concrete application requires validation of the NBS/NCM, the tax regime, credits, and current regulatory acts with a qualified professional. Tax rate estimates were used only to demonstrate the methodology. |
References
BRAZIL. Constitutional Amendment No. 132, of December 20, 2023. https://www.planalto.gov.br/ccivil_03/constituicao/emendas/emc/emc132.htm
BRAZIL. Complementary Law No. 214, of January 16, 2025. Establishes IBS, CBS, and Selective Tax. https://www.planalto.gov.br/ccivil_03/leis/lcp/lcp214.htm
BRAZIL. Complementary Law No. 227, of January 13, 2026. Establishes the IBS Managing Committee and amends Complementary Law No. 214/2025. https://www.planalto.gov.br/ccivil_03/leis/lcp/lcp227.htm
FEDERAL REVENUE OF BRAZIL.
Understand the Consumption Tax Reform (Reforma Tributaria). https://www.gov.br/receitafederal/pt-br/acesso-a-informacao/acoes-e-programas/programas-e-atividades/reforma-tributaria-do-consumo/entenda
BRAZILIAN FEDERAL REVENUE.
Guidelines for the 2026 Reforma Tributária. Updated on May 6, 2026. https://www.gov.br/receitafederal/pt-br/acesso-a-informacao/acoes-e-programas/programas-e-atividades/reforma-tributaria-do-consumo/orientacoes-2026
IBS STEERING COMMITTEE.
CGIBS Resolution No. 6, of April 30, 2026. Regulates the IBS. https://www.cgibs.gov.br/upload/arquivos/202604/30084927-res-cgibs-n-6-30-abr-2026-regulamenta-o-ibs.pdf
Access to electronic sources on: Aug. 24, 2026.